
Reasons a Potty Trained Child Has Accidents & How to Help
This post contains affiliate links. As an Amazon Associate, we learn from qualifying purchases
A potty-trained 4-year-old suddenly having accidents is usually a sign of either physical constipation putting pressure on the bladder or a psychosocial stressor disrupting their routine. The clinical term is daytime urinary incontinence, defined as involuntary voiding two or more times per month. Before worrying, track patterns for two days. If accidents are paired with hard stools, belly pain, or occur during times of change, you have a clear starting point.
This definition matters because it separates a true medical pattern from a random mishap. A one-off accident because they were glued to the swings is normal. A pattern of puddling multiple times a week is a signal.
What follows is a breakdown of the two main branches, physical and psychological, with the diagnostic steps to tell them apart. You’ll get the sourced numbers on normal bladder function, the exact method for a voiding diary, and the non-punitive responses that actually work.
Key Takeaways
- Daytime incontinence is a medical pattern, not a behavioral choice. It’s defined as two or more accidents per month.
- Constipation is the leading physical cause, implicated in 70-80% of cases. Hard stool presses on the bladder, creating false urgency and preventing complete emptying.
- Bladder capacity grows by about 30ml per year after age three. A 4-year-old’s bladder holds roughly 150ml, but their kidneys produce about 60ml of urine per hour.
- Stress is the most common psychosocial trigger. A new sibling, school change, or even academic pressure can overwhelm a child’s ability to attend to bodily signals.
- A two-day voiding and stooling diary is your most powerful tool. It provides objective data for you and any healthcare professional, moving the conversation from guesswork to evidence.
The Medical Definition: When Is It an “Accident” vs. Incontinence?
The first step is to define the problem with the precision a pediatrician would use. This stops you from reacting to noise and lets you focus on the actual signal.
Urinary incontinence in children is clinically defined as involuntary voiding of urine two or more times per month during the day or night. This comes from the Merck Manual Professional edition, a peer-reviewed medical reference. That frequency threshold is critical. A single wet day after a long car ride is an accident. Wet pants three afternoons in a week is a pattern that meets the definition for evaluation.
By age four, about 90% of children have achieved daytime continence. So a regression in a previously trained child stands out. But “regression” itself has a specific meaning in child development, it’s the loss of a previously mastered skill. In potty training, that means a clear pattern of accidents, not a one-off.
A voiding diary, recording timing, frequency, and volume of voids for a minimum of two days, is the cornerstone of clinical assessment for childhood incontinence.
This diary is how you move from “my kid is wetting again” to “my kid voids small amounts every 90 minutes and has a large bowel movement every four days.” It turns emotion into data.
Common Physical Culprits (And Why Constipation Is King)
When a potty-trained child starts having accidents, your first stop should be a physical check. The body’s systems are interconnected in ways that aren’t always obvious.
The Constipation Connection
This is the number one issue to rule out. A urology nurse practitioner from Children’s Health states that 70-80% of daytime wetting with a physical cause links back to constipation. The mechanics are straightforward: the rectum is located directly behind the bladder. When it’s packed with hard, retained stool, it presses on the bladder wall.
This pressure does two things. First, it reduces the bladder’s functional capacity, making it feel full faster. Second, it irritates the bladder muscle, causing sudden, uncontrollable urges, a condition called overactive bladder. The child feels a “I have to go RIGHT NOW” sensation and often doesn’t make it.
A constipated toddler typically poops fewer than twice per week, and the stool is often hard, pebble-like, or unusually large. Softer stool can sometimes leak around the blockage, leading to skid marks in the underwear (encopresis), which can be mistaken for a potty accident.
“Small” or Overactive Bladders
Some children have bladders that are structurally normal but functionally smaller. They fill quickly and contract before they’re truly full, leading to urgency and frequency. This isn’t a character flaw; it’s a neurological wiring where the bladder muscle (detrusor) is overactive.
Other children simply have a maturational delay in the coordination between the bladder muscle and the sphincter. They haven’t yet mastered the subconscious skill of holding on while the bladder fills.
Urinary Tract Infections (UTIs) and Other Causes
A UTI irritates the bladder lining, causing painful urgency, frequency, and sometimes accidents. It’s often accompanied by other symptoms like fever, stomach pain, or crying during urination. This is usually a discrete episode, not a chronic pattern.
More rarely, anatomical abnormalities or conditions like diabetes (causing excessive urine production) can be underlying causes. These are why a persistent issue warrants a pediatrician’s visit.
| Physical Cause | Key Signs | Typical Age | First Action |
|---|---|---|---|
| Constipation | Poops <2x/week, hard stools, belly pain, skid marks | Any age, common at 3-5 | Increase fluids/fiber, consider stool diary |
| Overactive Bladder | Sudden “emergency” urges, squatting/holding maneuvers, frequent small voids | 4-7 years | Scheduled toilet sits every 2 hours |
| UTI | Dysuria (pain), fever, foul-smelling urine, sudden onset | Any age | Pediatrician visit for urinalysis |
| Maturational Delay | Never achieved long dry spans, may also have nighttime wetting | 4-6 years | Patience, scheduled voids, rule out other causes |
Psychological and Behavioral Triggers

If you’ve ruled out the physical, the next branch to explore is the psychological. A child’s brain can only handle so many new demands at once.
Stress and Life Changes
Stress is the most common psychosocial reason for regression. The parts of the brain that manage anxiety and the parts that pay attention to bladder signals are in competition. When stress wins, accidents happen.
The triggers aren’t always major. They can be: * A new daycare or classroom. * A new sibling. * Parental conflict or a change in family dynamics. * Moving houses. * Even a vacation disrupts the familiar routine and bathroom environment.
For older four-year-olds in preschool, academic stress or social anxiety can be the culprit. A child afraid of missing out during playtime or scared of the school bathroom will delay until it’s too late.
Attention and Developmental Factors
For children with ADHD, the issue is often distraction, not defiance. They become so hyper-focused on an activity that the bladder’s signal doesn’t break through. The fix isn’t punishment; it’s a schedule. A mandatory toilet break every two hours, whether they “feel it” or not, preempts the accident.
Similarly, children on the autism spectrum may regress if they were potty-trained before they were fully developmentally ready. For some children with ASD, full readiness might not come until age 8 or later. What looks like a regression might actually be a mismatch between expectation and ability.
Where this goes sideways: Scolding or shaming a child for stress-related accidents. The anxiety you add compounds their existing stress, locking in the cycle. They need calm support, not more pressure.
The 2-Day Voiding Diary: Your First Diagnostic Tool
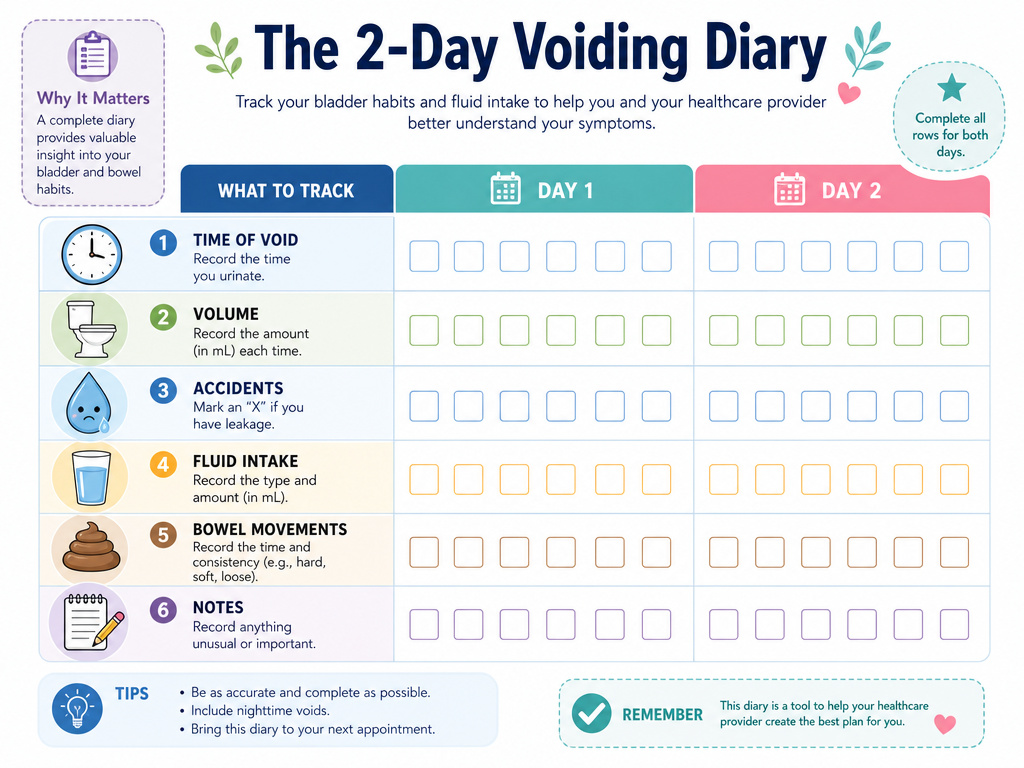
Before you call the doctor or overhaul your routine, gather data. A voiding diary cuts through the worry and gives you something concrete to work with, or to bring to a professional.
Here’s how to do it. Track for two weekdays (weekends can be atypical):
- Time of each void: When they peed.
- Estimated volume: Use terms like “small,” “medium,” “full potty bowl.”
- Accident timing: When and where any wetting occurred.
- Fluid intake: What they drank and when.
- Bowel movements: Time, size (small/medium/large), and consistency (hard/soft/mushy).
- Notes: Was there urgent dancing? Did they refuse to go?
You’re looking for patterns. Is every accident preceded by a 3-hour dry spell? That suggests holding too long. Are they voiding tiny amounts every hour? That points to an overactive or functionally small bladder. Are the accidents always after school? That screams environmental stress.
This diary is also the tool a pediatric urologist will ask for first. Walking in with two days of data transforms the conversation from “My kid has accidents” to “My kid voids small amounts hourly and hasn’t had a bowel movement in five days.”
How to Respond and Get Back on Track
Your reaction sets the tone. The goal is to solve the problem without creating a new one centered on shame and anxiety.
If You Suspect a Physical Cause
- Address constipation aggressively. Increase water intake dramatically. Pears, prunes, peaches, and fiber-rich cereals are your friends. If diet isn’t enough within a few days, talk to your pediatrician about a gentle, pediatric-formulated stool softener like Pedia-Lax or a generic polyethylene glycol 3350. Clearing the backlog is often the only fix needed.
- Implement a mandatory toilet schedule. Every two hours, they sit. This isn’t a negotiation. It retrains the bladder to fill more fully and empties it before urgency strikes. Use a visual timer.
- Ensure complete emptying. Teach them to relax on the toilet, take their time, and maybe count to 20 after they think they’re done. Rushing leads to retained urine, which can cause UTIs and more urgency.
If You Suspect a Psychological Cause
- Talk, but don’t interrogate. Use open-ended, non-blaming questions during calm moments. “I noticed going to the bathroom at school has been tricky lately. What’s that like for you?”
- Reinstate your old reward systems. Dig out the sticker chart or the treasure box. You’re not bribing; you’re providing positive reinforcement for a skill that’s gone offline.
- Reduce pressure, not supervision. Drop the sighs, the frustrated changes, the “again?!” comments. Handle clean-ups calmly and matter-of-factly: “Oops, your pants are wet. Let’s get you clean.” Then move on.
- Problem-solve environmental hurdles. If school is the trigger, send a doctor’s note requesting unrestricted bathroom access. Pack an easy-change outfit in a zip-top bag for their backpack.
When to Call the Doctor
Seek professional advice if: * The voiding diary shows a clear physical pattern (constant urgency, infrequent BMs). * You see blood in urine or stool. * There’s any pain with urination or fever. * Constipation doesn’t resolve with basic dietary changes. * The accidents persist for more than a month despite your consistent, calm interventions. * Your child is over age 6 and still experiencing daytime incontinence.
A good starting point is your pediatrician. For complex cases, they may refer you to a pediatric urologist or a voiding dysfunction clinic, which specializes in these exact issues.
Frequently Asked Questions
Is this a sign of a serious medical problem?
Usually not. Most often, it’s constipation or stress. However, persistent daytime incontinence beyond age 6, or any signs of pain, fever, or blood, warrants a medical evaluation to rule out anatomical or neurological issues.
Could my child be doing this on purpose for attention?
Deliberate wetting is rare. When it happens, it’s almost always a distress signal for significant psychological stress or trauma. The response should be compassionate investigation, not punishment. Assume it’s not intentional until proven otherwise.
Should I go back to pull-ups or diapers?
This is a judgment call. For some kids, returning to training pants during a regression reduces laundry and shame, allowing for a pressure-free reset. For others, it feels like a major step backward and undermines their big-kid identity. If you use them, frame it as a temporary helper, not a demotion.
How long will this regression last?
It depends on the cause. A stress-related regression from a known event (like a move) often resolves in 2-4 weeks with support. Constipation-related accidents can stop within days of clearing the bowel. If there’s no clear fix and it drags on beyond a month, professional guidance is key.
My child also wets the bed. Is this connected?
They can be related but are often separate. Nighttime wetting (nocturnal enuresis) has strong genetic links and is related to deep sleep and hormone production. Daytime incontinence is more about bladder function and conscious control. However, constipation can worsen both. Treating daytime issues first is standard, as achieving daytime dryness often helps night training fall into place later.
Before You Go
A potty-trained 4-year-old suddenly having accidents is a frustrating puzzle, but it’s almost always solvable. Start with the two-day diary, it’s the flashlight in a dark room. Rule out constipation first; it’s the quiet culprit in most cases. If the diary points to stress, double down on calm connection and revisit the potty training chart that worked before.
This isn’t about willpower. It’s about physiology meeting psychology. Your job is to be the detective, not the judge. With observation, patience, and sometimes a pediatrician’s help, the dry days will return.
